
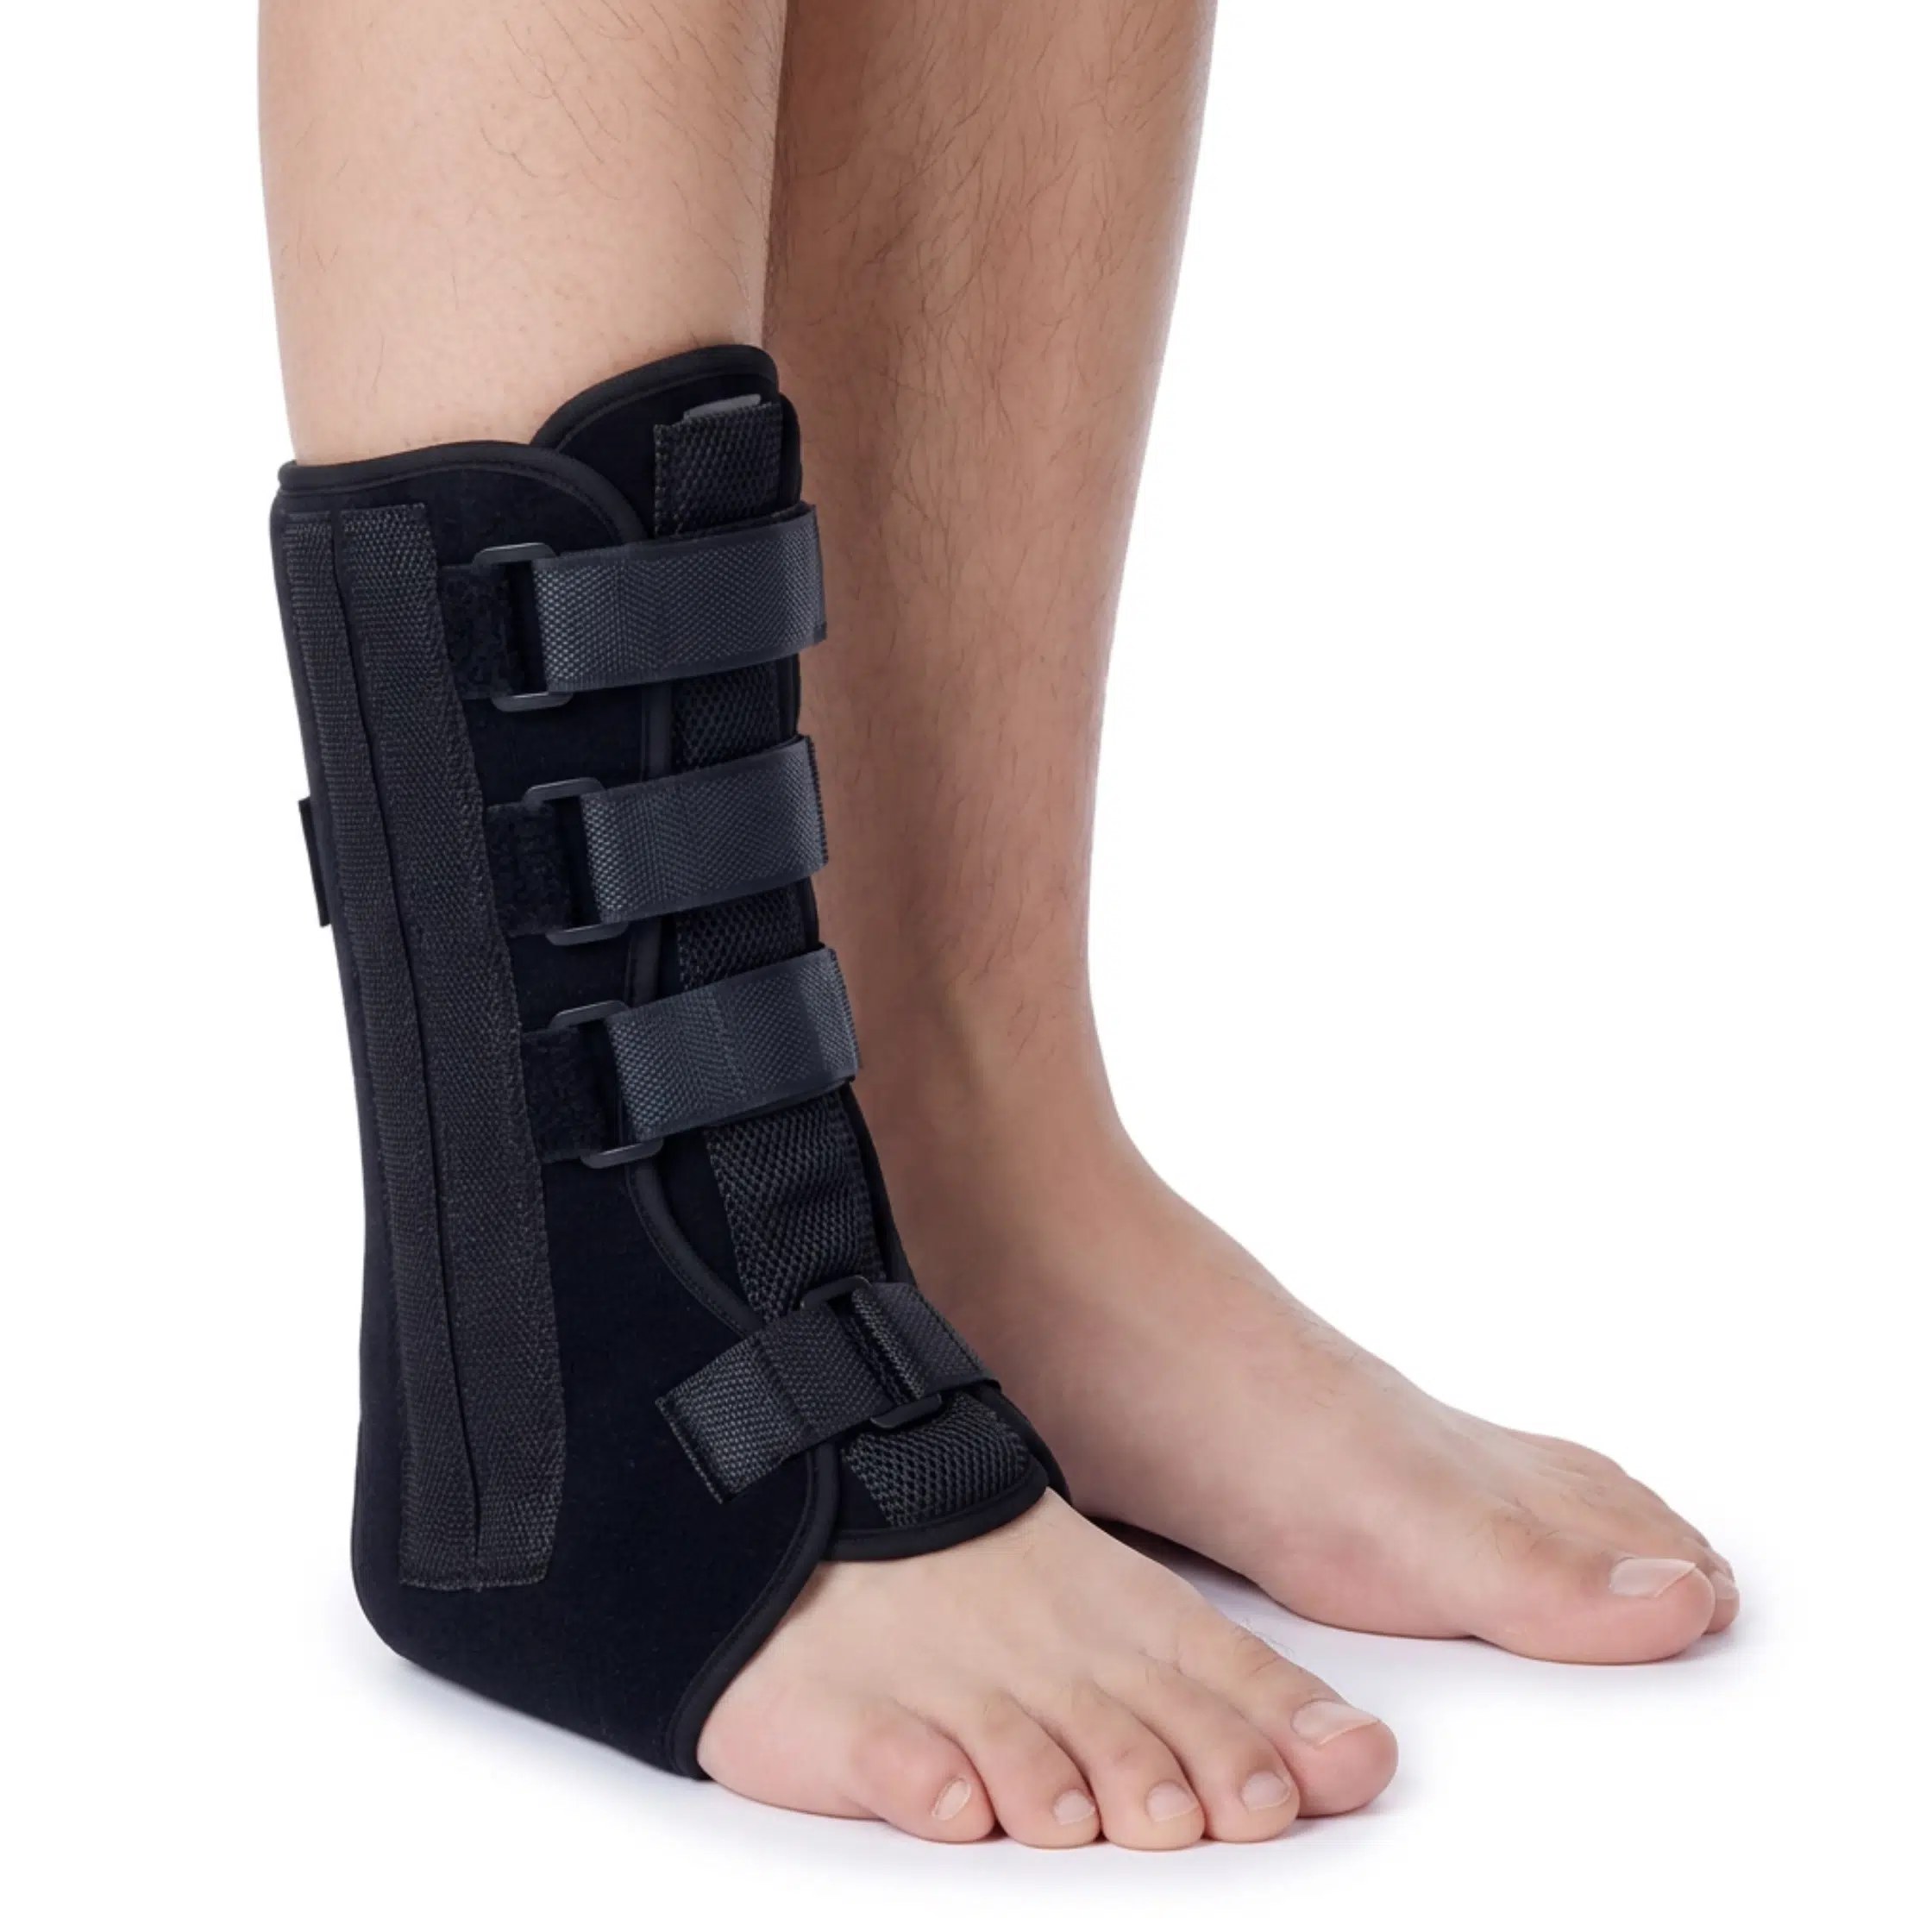


Ankle Splint Foot Brace & Post-Op Cast Support for Ankle Sprains, Fractures, Achilles Tendonitis & Drop Foot
£14.99inc VAT
- A supportive ankle and foot brace with a firm outer frame and flexible aluminium splints.
- Suited to adults recovering from an ankle sprain or strain, and to the weeks after a fracture, cast or ankle operation once a rigid boot is no longer needed.
- Also for ankles that keep giving way, tendons that flare with activity, and a foot that doesn’t lift properly at the front.
- Side splints resist the inward and outward roll that strains ankle ligaments.
- Front and back splints limit how far the ankle bends forwards and backwards, while still allowing a normal walking stride.
- A rear splint runs up over the Achilles tendon and helps hold the foot closer to a right angle with the lower leg.
- Reaches to roughly mid‑calf, which spreads pressure over a larger area of the leg.
- Several adjustable straps, each with its own buckle, so support and compression can be set through the day.
- Padding around the ankle bones and heel helps reduce rubbing over bony points.
- Universal design that fits either foot, available in three UK sizes from UK 3 to UK 11.
- Lightweight and slim enough to wear inside a walking shoe or a trainer with a looser fit.
- Usually worn when you’re on your feet or bearing weight, and taken off for rest and overnight.
- It doesn’t replace the weight‑bearing or activity limits your clinician has given you, and it isn’t intended for sleeping unless a clinician advises it.
- Check the skin regularly. Redness that doesn’t fade, blisters, broken skin, or new numbness or tingling mean the fit needs reviewing.
- Not intended for use in pregnancy. If you have reduced sensation, fragile skin, an open wound, circulation problems, or a history of blood clots, check with a clinician before using it.
Living with ankle and foot problems
When your ankle is sore or unsteady, you might start moving more carefully without meaning to. Having to think about every step makes even a short walk feel like hard work, and keeping that level of attention up is draining.
Often, the ligaments, tendons, joints, or nerves around the ankle and foot are either recovering from a clear injury or adjusting to long-term wear, strain, or changes in how the nerves and muscles control movement. When those tissues are painful, overstretched, or not working as they should, moving normally can feel uncomfortable. Putting your full weight through the leg may hurt, and the ankle can feel unstable.
An ankle–foot brace is one option that can make walking feel steadier and more secure while those tissues recover and settle down.
What is happening in your ankle and foot
Your ankle and foot are designed to move and to carry your weight. Every step, every shift of weight, and every minute you spend standing or walking sends force through your ankle. That force has a name: load. Ligaments are strong bands that connect one bone to another. They limit how far the joint can tilt or roll. Tendons connect muscle to bone and help control movement. Cartilage covers the ends of bones so they can glide smoothly against each other. Nerves carry signals that tell your muscles when to work. They also give you a sense of where your foot is and how it is moving.
When any of these tissues are injured, strained, worn, or not working as they should, walking and standing can become uncomfortable, and your foot may feel unstable. The muscles in your lower leg control how your foot moves. Their tendons attach to the bones around the ankle and foot. The Achilles tendon sits at the back of the ankle and links the calf muscles to the heel bone. It works with every step, helping you push off the ground and lower your heel smoothly. If you walk or run more than usual, or suddenly change how active you are, small areas within these tendons can become irritated and sore.
A strong band of tissue called the plantar fascia runs under the sole of your foot. It stretches from the heel bone to the toes and helps support the arch. Standing for long hours on hard floors, changing your footwear, carrying extra body weight, or suddenly walking or running more can strain this band. The strain often appears near where the band attaches to the heel. This often causes sharp heel pain with the first steps after rest. After those first steps, the sharp pain often fades into an ache that builds as you stay active.
Over time, the smooth cartilage covering the ends of the bones can wear down. In arthritis, that cartilage becomes thinner and rougher, and the lining of the joint can become inflamed. Your ankle may then feel stiff and sore, especially after rest or after long periods of standing or walking.
For some people, nerve or muscle problems mean the front of the foot doesn’t lift properly. This is often called drop foot. The toes can catch on the ground, which can lead to trips or falls. To clear the foot, you may have to lift your leg higher than usual. That can be tiring, and it places extra strain on other joints.
Your daily habits can also add to the load on your ankle and foot. Walking or running on sloping or uneven ground, standing for long periods with your weight on one leg, or wearing footwear that offers little ankle support for much of the day can shift more work onto certain muscles and tendons. Over time, these habits can create a low-level ache that gets worse when you do more.
If you recognise your problem
Common ankle and foot problems behave differently from one another, and each needs a slightly different approach. Each entry explains what is happening, what keeps the problem going, and how it’s usually managed. Open the one that matches your experience.
Why an ankle–foot brace can help
People use an ankle–foot brace for several common reasons: after a recent sprain, when the ankle keeps giving way, when a tendon flares on stairs, when a joint stiffens with use, in the weeks after a cast, or when the front of the foot does not lift properly. In each situation, the ankle and foot are asked to do more than the surrounding tissue can handle reliably at that time. A brace helps by changing what that tissue has to cope with.
Your ankle does a demanding job. It bends forwards, backwards, and from side to side while carrying your body weight, and it repeats those movements thousands of times a day. When ligaments are healing, tendons are irritated, joint surfaces are worn, or the nerves and muscles that control the foot are not working reliably, those everyday movements become harder than the tissue can manage comfortably.
A brace changes how load and movement pass through the ankle. It can hold the joint closer to a comfortable middle position, so the ankle does not move as far in ways that strain healing or irritated tissue. It can also make the foot feel steadier, which reduces the constant corrections that weak, slow-reacting, or tired muscles have to make. Gentle, even compression can help limit the swelling that builds up through the day, which is often what makes the joint feel tight and heavy.
For some people, the main benefit is more direct: the brace keeps the foot lifted. If the front of the foot drops, holding it up makes it easier for the toes to clear the ground as the leg swings forward when you walk.
None of this replaces what your body needs to do to recover. A brace does not strengthen muscles, rebuild ligaments, or reverse joint wear. What it does is limit the strain on those tissues while they heal, and make walking feel more stable in the meantime.
How the FootReviver Ankle Splint Foot Brace is designed to help
Structure and alignment
The brace is built around a firm frame that wraps the lower leg and ankle and rests on a stable base beneath the foot. It reaches to roughly mid‑calf. Once the front panel is in place, it surrounds the ankle on all sides. The padding, the straps, and the rear splint that runs up the back over the Achilles tendon all stop at the same height. That height keeps the brace in place without the top edge pressing into your leg.
Inside the frame, and inside the front panel, sit flexible aluminium splints. There are two down the outer side of the ankle, two down the inner side, one in the front panel, and one running up the back over the Achilles tendon. The side and back splints come pre‑shaped to follow the natural line of your lower leg and ankle, so they rarely need adjusting. The front splint sits in a panel that lifts off, so you can gently mould it to follow the front of your shin when you first fit the brace.
These splints are firm enough to hold against a sudden or forceful movement, yet flexible enough to bend a little as you walk. So the brace feels supportive without being completely rigid.
Together, the frame and the splints keep the ankle and foot closer to a straight‑ahead position. The side splints resist the inward roll that causes most outer‑ankle sprains, and the outward roll that strains the inner side. The front and back splints control how far the ankle bends forwards and backwards, while still allowing a normal walking stride. Because the brace runs up to mid‑calf rather than stopping at the ankle, the splints spread support over a longer section of the leg. That spreads pressure over a larger area, and it lets the ankle move through the range it needs for walking without twisting or bending too far. That lowers the demand on the tissues that are still repairing.
Straps and adjustability
Several buckled straps run across the foot, around the ankle, and up the lower leg. They hold the brace closely against your leg, so it moves with you instead of slipping or rubbing.
Each strap has its own buckle, which means you can tighten them one by one to suit how the brace feels on the day. You might want firmer support around the ankle joint for a longer walk, and gentler tension for moving around the house. That flexibility lets you match the level of support and compression to what you are doing, and to how much swelling you have at that point in the day. The straps are laid out so that most people can put the brace on themselves, with little or no help.
Compression and swelling control
The brace applies steady compression around the ankle and foot. This helps limit swelling and eases the heaviness or tightness that many people notice building by the end of the day.
Once swelling is better controlled, the ankle usually has more room to bend and straighten as far as feels comfortable. That makes early movement easier when the joint feels stiff, and it helps you keep the ankle protected while you rebuild strength and movement, following advice from your doctor or physiotherapist.
Positioning and movement
One of the brace’s main jobs is to hold the foot at a steadier angle to the lower leg, and to control side‑to‑side roll. The flexible splints at the sides, front, and back resist sudden twists and extreme bending, while still allowing a normal walking movement. That protects tissues that react badly to sudden or excessive movement.
If your ankle tends to roll inwards after a sprain, the side splints help resist that roll. If you have had sprains before, or feel the ankle might give way, this positioning reduces sudden inward or outward twists, particularly on uneven or sloping ground. After a fracture or a period in a cast, the splints and frame can make the ankle feel more stable during the early stages of putting your full weight through the leg again. With drop foot, holding the foot up helps the toes clear the ground and may reduce tripping. The rear splint over the Achilles also limits pointing the foot down hard, which can be uncomfortable when the tendon or the area after surgery is sensitive, while still allowing a normal push‑off.
Comfort and fit
The brace uses lightweight, breathable materials and has a slim profile. Air can circulate around the skin, and moisture is less likely to build up than inside a heavier, fully enclosed boot. Padding around the ankle bones and heel spreads pressure and reduces rubbing over these bony points. That matters especially when you wear the brace for long periods, because it lowers the risk of skin irritation on days when you are on your feet for hours. Even so, it is still worth taking the brace off at intervals to relieve pressure on the skin.
Because it is not bulky, many people can wear it inside a walking shoe, or a trainer with a looser fit — anything you can open wide and adjust. If the brace feels tight under the laces, going up half a size is usually enough. Once your doctor or physiotherapist says it is suitable, wearing it in everyday shoes makes it easier to use at home, outdoors and at work after a rigid boot is no longer needed.
When this type of brace helps — and when to check first
The FootReviver Ankle Splint Foot Brace tends to suit three broad situations.
The first is an ankle that needs protecting while it recovers — after a sprain or strain, or in the weeks after a fracture or an operation when a cast or boot has come off. Here the brace provides meaningful support. It holds the ankle in a safer position while the tissue underneath rebuilds, and that protection matters most in the early weeks when the repair is still fragile.
The second is an ankle or tendon that has troubled you on and off for some time. That covers a joint that does not feel fully reliable, or an area where certain activities reliably trigger symptoms. In this situation, the brace is mainly for day‑to‑day support. It helps on the days that ask more of your ankle, and it supports whatever else you are doing; it does not replace it.
The third is a foot that does not lift properly at the front, known as drop foot. Holding the foot up in this position makes it easier for the toes to clear the ground as you walk, which can reduce catching and tripping. The brace does not treat the underlying nerve or muscle cause, so assessment by a doctor or physiotherapist comes first.
It helps to know which of these situations you are in, because it changes what you can expect. For short‑term recovery, the brace tends to be most useful early on and needed less as strength returns. For longer‑standing problems, it tends to stay useful as extra support, for years rather than weeks, but it does not replace treatment or exercise. For drop foot, it is one part of managing walking safely while the cause is being investigated and treated.
For some problems, other measures often help more than a brace. Supportive footwear, insoles that position the foot, exercises to build strength and flexibility, spreading activity more evenly across the day, and weight management where it is relevant all address the underlying causes rather than the symptoms. If you are dealing with heel or arch pain, or with ankle arthritis, those approaches are likely to make the bigger difference day to day, and the brace supports them rather than replacing them. It is best thought of as extra support for the situations that tend to trigger symptoms — a longer walk, a busy day on your feet, a flare‑up.
There are also people who should check with a clinician before using any brace of this kind. If you have reduced sensation in your foot or leg, fragile skin, an open wound, or a problem with your circulation, speak to a clinician first. If your ankle or foot has been injured recently and has not been assessed, get it assessed first. And if you are not sure which situation you are in, a doctor, physiotherapist, or podiatrist can help you work out which situation applies.
Getting the fit right
Choosing a size
The FootReviver Ankle Splint Foot Brace comes in three sizes, matched to your usual shoe size:
-
- Small — UK 3 to 5
-
- Medium — UK 5 to 8
-
- Large — UK 8 to 11
Getting the size right matters. A brace that’s too small may dig in, cause sore spots, or restrict circulation. One that’s too large may not control movement properly and could slip. The ranges overlap at UK 5 and UK 8, so if your shoe size sits at one of those points, if your foot tends to swell, or if you’re not sure, check with a doctor, physiotherapist or podiatrist who knows your ankle. Think about the socks you plan to wear underneath, too, because a thicker sock takes up more room inside the brace. At a boundary size, the slightly larger option may feel more comfortable, provided the straps can still be tightened enough to control movement. The design is universal, so the same brace fits either foot as long as the size is correct.
Putting the brace on
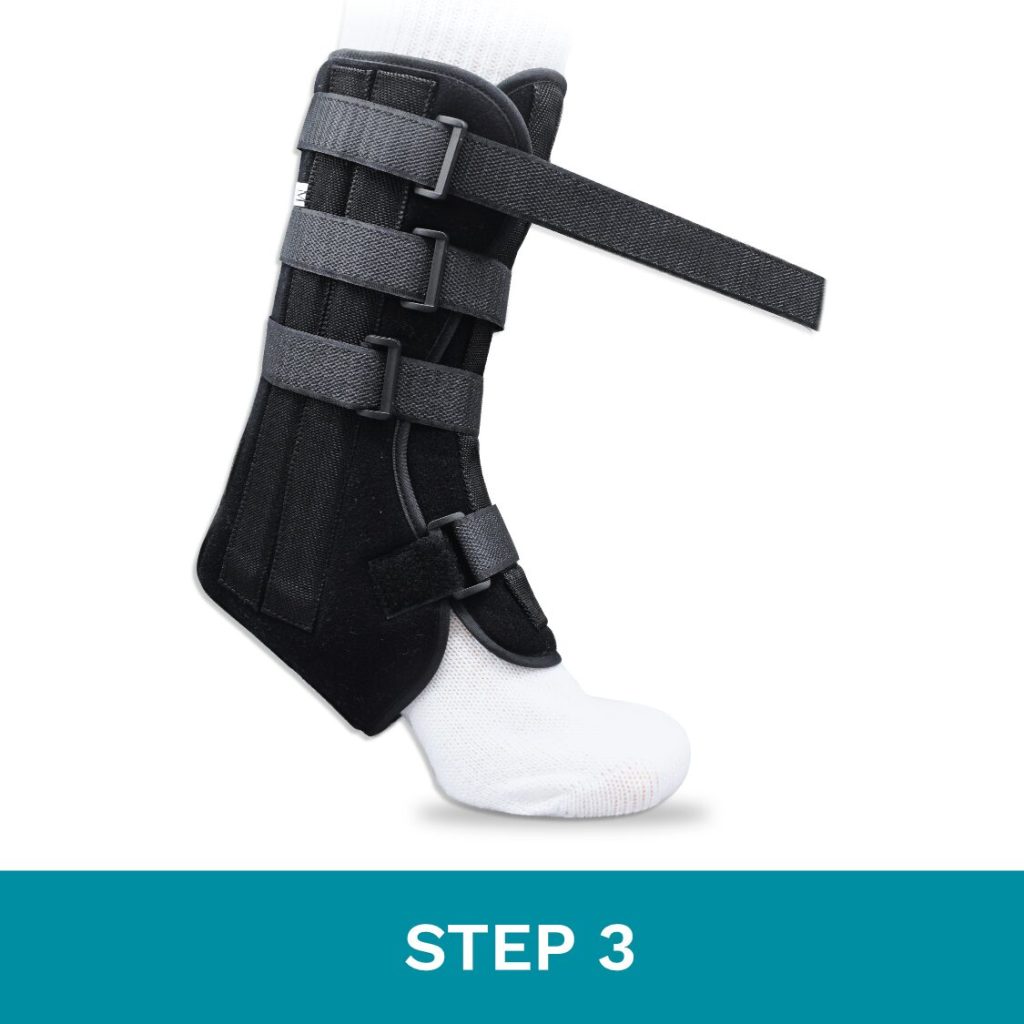
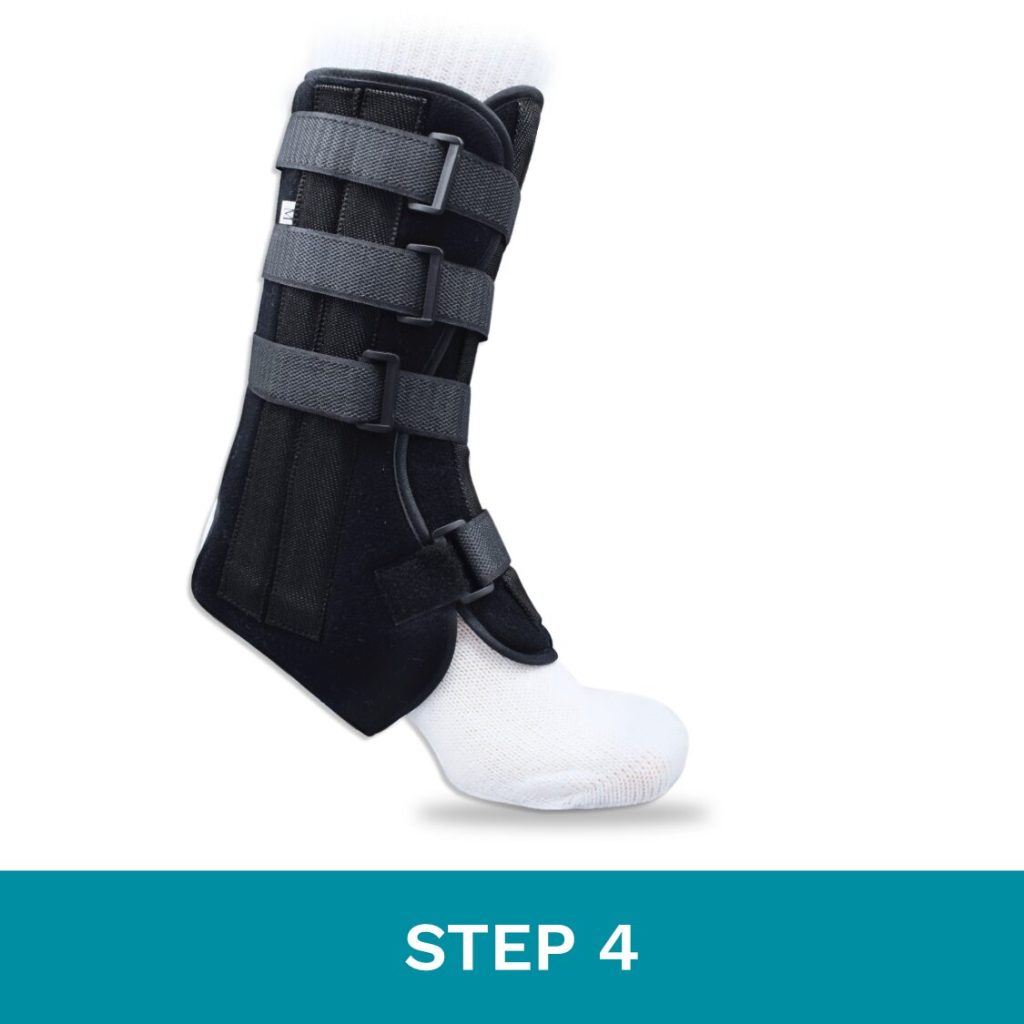
To get the most benefit, position the brace correctly before tightening anything. Your heel should sit right back in the heel section, and your foot should rest flat on the base so the ankle sits roughly at a right angle.
Fasten the straps starting near the ankle joint, then work up the leg and along the foot. Each strap should feel firm enough to give support, but not so tight that it causes pain, pins and needles, or changes the colour of your toes. The first few times, it may take a couple of attempts to find a comfortable, secure fit — especially if your ankle is still swollen. Most people find it easier after doing it a few times.
The front panel can be gently shaped to follow the front of your shin before you tighten the straps over it. Wear a thin or compression sock under the brace to protect the skin, as long as the brace and footwear still fit without feeling tight.
Work through it in the same order each time: thread the straps fully through the buckles, slip your foot in while placing the front panel against the front of your foot and lower leg, then tighten the straps to the level of support and compression you need. Check that the brace sits securely without being so tight that it restricts the blood flow to your foot.


How it should feel
When the brace fits well, your ankle should feel more secure, especially in the directions that previously felt weak or painful. You should notice a firm, even hold around the joint rather than sharp pressure in one spot. Your toes and the part of your foot beyond the brace should stay warm, with normal sensation.
You should still be able to move your ankle within the safe range your doctor or physiotherapist has advised for your stage of recovery. At first, the brace may feel slightly unfamiliar because it guides your movement differently, but most people adjust to it quickly. If it digs in, slips, or fails to limit the movements causing your discomfort or instability, the fit or size may need checking.
Common fitting problems and checks
If your heel isn’t fully seated at the back of the brace, the ankle won’t be held securely and rubbing is more likely. Straps that are much tighter in one area than another can also create pressure points. After wearing the brace for a few minutes while standing or walking, check how it feels and make small adjustments.
If your ankle and foot swell at certain times, such as later in the day, you may need to loosen or re‑tighten the straps slightly. Check the skin underneath after each long wear, particularly in the first week or two and any time the fit changes. Redness that doesn’t fade once the brace is off, blisters, sore spots or new numbness or tingling all mean the fit needs looking at, and you should ask a doctor, physiotherapist or podiatrist to review it.
Using the FootReviver Ankle Splint Foot Brace day to day
Early after injury or surgery
In the first days and weeks after a sprain, fracture or operation, the main aim is to protect healing tissues. At this stage, your doctor or physiotherapist will usually set clear limits on how much weight you can place through the foot and how far you can move the ankle.
If a brace like this is recommended, you may be asked to wear it whenever you’re standing or walking. It keeps the ankle in a safer position and adds support as you begin to put weight through it again. It can also help you move from a rigid cast or boot towards more natural walking. It should never be used to exceed the weight‑bearing or activity limits you’ve been given.
Rehabilitation phase
As pain and swelling settle and movement becomes easier, the focus usually shifts to rebuilding strength, flexibility and control. The brace can still be useful here as you start to do more.
You may be advised to wear it for longer walks, uneven ground, or exercises that challenge your balance. In safer situations — controlled exercises on flat ground, or short tasks at home — you might spend short periods without it, so your muscles and joint can begin to manage without constant external support. The right balance between time with and without the brace depends on your progress, and your physiotherapist or doctor can guide you on when to rely on it and when to practise short periods without it.
This is often the stage where people start to notice the pattern changing. The brace gets used less indoors and more outdoors. Progress here tends to be uneven rather than a straight line. A good week doesn’t mean you’re ready to stop using it, and a difficult week doesn’t mean you’ve gone backwards.
Long‑term use for instability and arthritis
For ongoing problems such as long‑standing instability or ankle arthritis, the brace can play a part in day‑to‑day management rather than recovery. Many people choose to wear it on days when they expect to be more active, when symptoms are worse, or for tasks that usually bring on pain or a sense that the ankle might give way.
On days when you’re doing less, or when you’re only doing short, low‑demand activities at home, some people manage without the brace, relying instead on supportive footwear, any recommended insoles, and spreading activity sensibly through the day. How often you use the brace, and in which situations, is best decided with a doctor, physiotherapist or podiatrist who understands your ankle and your general health.
For long‑term conditions, the brace is a management tool rather than a short‑term aid, and you may keep using it on and off for years. That’s a normal pattern for this kind of problem, not a sign that something has gone wrong.
Sport and higher‑risk activities
With your doctor or physiotherapist’s agreement, the brace can sometimes be worn during sports or activities that involve running, jumping or quick changes of direction. Its structure and strap system can help reduce the risk of a sudden roll or twist during those movements.
It isn’t designed for unrestricted, high‑impact twisting sports or very deep ankle movements until you’ve been told you’re ready. Treat it as added protection within a gradual return to activity, not a substitute for rehabilitation. A safe return to sport depends on healed tissues, good strength and control, and a steady increase in training load. The brace supports that process rather than replacing the sport‑specific recovery work.
When to wear it and when to take it off
Most people wear this type of brace when they’re on their feet, bearing weight, or doing something that tests balance and stability. When you’re resting with your leg raised, or sitting or lying down for longer periods, there’s usually less need for it, and your skin and soft tissues benefit from time without pressure.
For most people, that break includes the night. This type of brace isn’t normally intended for sleeping unless your doctor or physiotherapist has specifically advised it. At night the ankle isn’t taking weight, so there’s nothing for the brace to do, and the skin and circulation benefit from a break from straps and compression.
Long stretches without a break — especially if you’re not moving much, or wearing the brace overnight — increase the risk of rubbing and pressure problems. Unless you’ve been clearly advised to wear it at night or for extended periods, take the brace off at intervals, check your skin, and let the skin air for a while before putting it back on. If you use compression socks or insoles alongside the brace, make sure your footwear isn’t too tight around the foot and ankle, because that can restrict blood flow. If you’re unsure how long to wear it, ask a doctor, physiotherapist or podiatrist.
What to expect as time goes on
Recovery looks different depending on what’s wrong with your ankle. After a straightforward sprain, you might notice a real difference within a few weeks, with the brace needed less often as strength and balance return. After a fracture or surgery, the timeline is longer and progress is measured in months. With arthritis or long‑standing instability, the brace stays part of your routine for longer, and what changes is how often and when you reach for it.
It’s important to be realistic about what any brace can do. It won’t cure an injury, rebuild strength, or reverse joint changes. What it can do is make movement safer and less painful while the rest of your recovery — exercises, footwear, activity changes, and any treatment your clinician has arranged — does its work. As strength and confidence grow, the brace usually becomes something you choose rather than something you rely on, and that shift is a good sign.
Looking after your brace
The FootReviver Ankle Splint Foot Brace is designed for regular use during recovery and for ongoing support when you need it. The frame and straps are built to cope with daily walking and standing.
Even so, check it from time to time. Look for fraying straps, loose stitching, or fastenings that no longer hold securely. Wipe the brace down if it becomes damp with sweat, let it air dry away from direct heat, and make sure it’s fully dry before wearing it again. Those small habits keep it comfortable and in good condition for longer.
Safety and when to seek advice
Acute injury warning signs
If you’ve recently injured your ankle or foot and you have very severe pain, the joint looks out of place, you can’t put any weight at all through the foot, or swelling comes on very quickly, seek urgent medical assessment before using a brace. These signs can point to a fracture or another serious injury that needs specific care rather than simple support.
Some pain and swelling in the first few days after an injury is expected, and it should ease with rest and appropriate management. If pain stays very high and doesn’t improve, or if swelling and discomfort are clearly getting worse rather than settling, ask to be reviewed by a doctor. Relying on a brace alone in these circumstances can delay treatment you need.
Circulation, nerve and skin concerns
Check the skin under the brace regularly, especially in the first week or two and any time the fit changes. Redness that doesn’t fade once the brace is off, blisters, broken skin, or any sign that the skin is being rubbed or damaged means the fit needs looking at, and you should seek advice.
A foot that turns unusually pale or blue below the brace, or that feels noticeably colder, numb or tingly, is a warning sign that circulation or nerve function may be affected. Remove the brace and get medical advice promptly.
Some people need to take more care than others with compression over a large area of skin. If you have diabetes, reduced sensation in the foot or leg, fragile skin, an open wound, a known circulation problem, or a history of blood clots, speak to a doctor or physiotherapist before using this brace, and ask how long to wear it in one stretch and how often to check your skin. Careful fitting, shorter wear periods to begin with, and regular skin checks are all part of using it safely in these situations.
This brace is not intended for use during pregnancy. If you are pregnant or have recently given birth and are considering a brace of this kind, speak to a doctor, physiotherapist or podiatrist first.
General health concerns
Fever, feeling generally unwell, or spreading redness and warmth around the ankle or foot can point to infection or another problem that needs checking. Speak to a GP or another clinician without delay.
If you suddenly find it difficult to lift your foot — especially alongside other symptoms such as weakness elsewhere in the leg, changes in sensation, slurred speech, facial changes, or a sudden loss of balance — seek urgent medical assessment. These signs can indicate a serious underlying condition. As a general rule, any new or unexplained symptom that does not settle is worth raising with a GP or physiotherapist.
Driving and this brace
Driving safely depends on moving your ankle freely, quickly and accurately to control the pedals. The brace is designed to limit ankle movement and hold the foot in a more fixed position, which can slow your reactions and reduce how precisely you press and release the pedals.
For that reason, you shouldn’t drive while wearing it. When you’re thinking about driving again after an ankle or foot problem, discuss it with your doctor and check the current rules for drivers. Only resume driving when you can control the pedals safely without the brace and you’ve been advised that it’s appropriate to do so.
A note on blood clots
This brace isn’t designed to prevent or treat blood clots or circulation problems such as deep vein thrombosis (DVT), and it must not be relied on for that. If you notice new or worsening swelling, pain or warmth in the calf, seek medical advice promptly.
Next steps
If the pain, stiffness or instability described here sounds familiar, and a doctor, physiotherapist or podiatrist has suggested that a brace of this kind is right for you, the FootReviver Ankle Splint Foot Brace is designed for exactly those situations. It holds the ankle in a steadier position, limits the rolls and twists that strain healing tissue, and lets you keep walking while the ankle recovers.
Before deciding, two practical things matter here. Check that the size matches your usual shoe size, and be clear about how the brace should be fitted and when it should come off. A steady, well‑fitted brace does far more useful work than one that is loose, tight, or worn at the wrong times. If you’re unsure whether this type of support suits your ankle, ask a GP, physiotherapist or podiatrist. They can tell you whether it’s appropriate for your stage of recovery and how to combine it with exercises, footwear changes and any other treatment you’ve been given. Used that way, it can help make walking feel steadier and more predictable while your ankle and foot recover.
Important information
The information on this page is general guidance about ankle and foot problems and about one type of ankle–foot brace. It isn’t a substitute for individual medical advice, diagnosis or treatment, and it can’t tell you what is happening in your own ankle.
If you’re unsure whether this kind of brace is right for you, or if you have more complex, new or unexplained symptoms, speak to a GP, physiotherapist, podiatrist or another appropriate clinician for personalised advice. No outcome is guaranteed, and recovery times vary from person to person.
5 Reviews For This Product
Fast & Secure Checkout Through Paypal
Pay with Paypal the secure payment gateway that accepts all credit and debit cards. Paypal is free and secure and no credit or bank information is ever stored or shared with us.
Fast Dispatch
Enjoy your items soon with quick dispatch via Royal Mail. Expect to have your items between 1-3 working days for domestic orders. 7-10 Working days for international orders.
Return Policy – 30 Day Money Back Guarantee
In the unlikely event, you are unhappy with your purchase you can return it within 30 days for a refund. Please contact us via the form on the contact us page to start your return.
To return an item please send it to: Nuova Health UK, 81 Highfield Lane, Waverley, Rotherham, S60 8AL. Please include a note with your order id so we know who to refund. Please retain your postage receipt as proof of postage. All that we ask is that the item is in the original packaging and unused.

by Elizabeth
Worth every penny! Gives a very good level of support and compression and has eased my sprained ankle a lot better than the brace I got from the NHS which was just painful to wear.
by Nick Lord
First hill walk for years without acute debilitating Achilles tendon pain So pleased. Had to give up Mountain Rescue because of the pain after a few hundred metres of walking. Will try again today further and steeper
by aneesa
is it good for sprain foot and the pain
by Paul
After twisting my ankle during a football game, I needed something to take the edge off. This little gem has been nothing short of fantastic – it’s durable, comfortable, and has made a world of difference. I’d give it a solid 10/10.
by TJ
really good 🙂